
Quick answer
There is no universal clinic marketing budget percentage that works for every practice. Build the budget backwards from available appointment capacity, priority services, acceptable acquisition cost and the clinic’s ability to answer and convert enquiries. Separate media spend from agency or team fees, content/creative, website/landing work, CRM/automation and measurement so you can see where growth is actually constrained.
Build My Clinic Growth BudgetKey takeaways
- Start with capacity and priority services, not a generic percentage of revenue.
- Separate ad spend, management, creative, website, CRM and measurement costs.
- A cheap lead is not valuable if it does not become a qualified booking.
- Fix response and landing-page leakage before increasing media spend aggressively.
- Reserve a controlled testing budget rather than constantly rebuilding the whole plan.
- Review budget by booked or attended patient economics where the data is available.
Experience & proof
Approved evidence you can inspect
These are anonymized, approved MDS Results & Proof summaries. They show operating context and outcome signals, not guarantees.
Multi-location specialty clinic
90-day operating window · GCC · demand-to-booking leakage
A specialty clinic group needed a clearer connection between demand generation, response discipline and booking visibility across multiple locations.
- Response ownership improved
- Campaign and inquiry sources were connected closer to booking outcomes
- Missed calls and follow-up gaps became reviewable signals
Hospital service-line growth
120-day build and optimization window · MENA
A healthcare network needed one operating view across service-line positioning, landing experiences, visibility and measurable inquiry movement.
- Priority service-line clarity strengthened
- Attribution structure was defined across campaign and organic signals
- Decision cadence became more focused on decision-ready KPIs
Client feedback
What clients said about the operating system
Anonymized feedback already published in the MDS Results & Proof experience. No star-rating or self-serving review schema is added.
“The difference was a system — not more posts.”
“We reduced response waste and started tracking bookings properly.”
“The market-entry plan gave us a clear path for cross-border demand.”
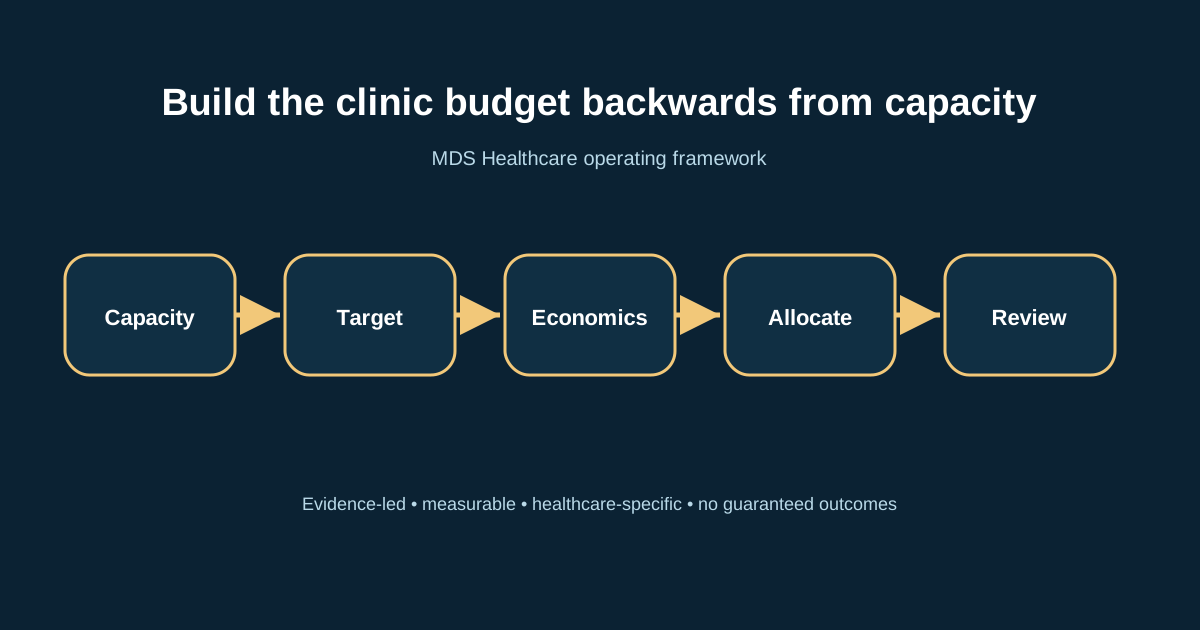
Build the clinic budget backwards from capacity
Budget decisions should connect service capacity, target bookings, acquisition economics, channel investment and conversion operations.
Start with appointment capacity, not an arbitrary percentage
A clinic cannot profitably buy more demand than it can answer, schedule and serve. Begin by identifying the services that need growth, the appointment capacity available for each one and the operational constraints that would prevent additional bookings.
High-value services may justify a different acquisition budget from routine services, but treatment value is not the only factor. Consider clinical suitability, consultation-to-treatment conversion, repeat visits, cancellations, payment mix and how quickly the team can follow up.
The budget should therefore be a planning model, not a benchmark copied from another specialty or country.
Capacity
How many additional qualified consultations can the clinic realistically handle?
Priority
Which services have strategic and clinical capacity for growth?
Economics
What acquisition cost can the clinic sustain based on verified treatment and conversion data?
Operations
Can reception, WhatsApp and scheduling convert the extra demand?
Separate the five budget layers
Many clinic owners compare only ad spend and agency fees. That hides the real system. A clinic may have enough media budget but weak pages, no tracking and slow response; increasing ads simply makes the leakage more expensive.
Create separate budget lines so leadership can see what is being bought and what each layer is supposed to improve.
A practical clinic marketing budget structure.
| Budget layer | What it funds | What to measure |
|---|---|---|
| Demand capture | Google Ads, paid social and other media | Qualified enquiries and attributable bookings |
| Organic visibility | SEO, local search and content | Relevant visibility, qualified organic enquiries |
| Conversion assets | Service pages, landing pages, CRO and creative | Conversion rate and enquiry quality |
| Response & CRM | Reception workflow, WhatsApp, automation and CRM | Response time, follow-up completion, booking movement |
| Measurement | Analytics, call tracking and reporting | Source-to-outcome confidence |
Build a backwards acquisition model
Use clinic data to work backwards. Start with the number of additional attended appointments or qualified consultations the clinic wants, then estimate the booking rate and the percentage of enquiries that are actually suitable. The model exposes whether the target is plausible before media spend is committed.
Do not turn rough assumptions into fake precision. Mark estimated inputs clearly, then replace them with observed data as the clinic improves tracking.
- 1
Set the service target
Define the treatment or service line and the additional capacity available.
- 2
Define a qualified enquiry
Agree what makes an enquiry relevant enough to count.
- 3
Measure enquiry-to-booking
Use CRM or booking records rather than memory.
- 4
Estimate acceptable acquisition cost
Base the limit on real economics, not competitor claims.
- 5
Allocate and test
Fund the channels and conversion layers required to reach the target, then adjust from evidence.
When the clinic should not increase ad spend yet
A clinic that misses calls, replies to WhatsApp hours later or sends paid traffic to a generic homepage has an operational problem before it has a media-budget problem. Increasing spend may create more apparent leads while bookings remain flat.
Use a leakage review before scaling. Test page relevance, mobile speed, call answer rate, WhatsApp ownership, booking availability, follow-up cadence and source tracking. Often the next pound or Egyptian pound should go into conversion infrastructure rather than another campaign.
- Campaigns generate clicks but landing pages do not match the advertised service.
- Reception cannot answer or return calls consistently.
- WhatsApp enquiries do not have an owner or follow-up standard.
- No one can distinguish a qualified lead from a low-intent message.
- Booking and attendance outcomes are not recorded by source.
- The clinic is already near capacity for the service being advertised.
Use proof and reviews to improve budget efficiency
Patients often compare credibility before they contact a clinic. Strong doctor pages, useful treatment information, genuine patient feedback and consistent local profiles can reduce uncertainty before the enquiry. That does not guarantee a lower cost per acquisition, but it can improve the quality of the decision environment the paid click enters.
Marketing-agency proof should be handled with the same discipline. Ask for case-study context, measurement windows and what was actually tracked. Avoid budgeting from screenshots of isolated lead costs that do not show booking quality or clinic operations.
Budget principle
Spend should follow the bottleneck. If the clinic cannot convert the demand it already has, spend first on the system that protects and measures the enquiry.
A monthly clinic budget review that supports decisions
Review the budget by service line and outcome. Look at spend, qualified enquiries, response, bookings, attendance or treatment starts where available. Separate direct attribution from influenced or unknown outcomes.
Keep a controlled test budget for new keywords, creatives, pages or audiences, but do not reset strategy every week. Stable measurement makes it easier to see whether performance changed because of media, conversion, operations or simple demand seasonality.
Keep
Channels and pages creating repeatable qualified progression.
Fix
Demand sources with strong intent but preventable conversion leakage.
Test
A small number of new messages, keywords or landing experiences.
Stop
Activity that repeatedly produces low-quality or unmeasurable outcomes.
Frequently asked questions
How much should a clinic spend on marketing in Egypt?
There is no universal amount that is credible for every clinic. Build the budget from service capacity, treatment economics, competition, current conversion performance and the number of additional qualified bookings the clinic can actually serve.
What is the difference between marketing budget and agency cost?
The marketing budget is the full investment across media, agency or team fees, content, creative, website/landing work, CRM, automation and measurement. Agency cost is only one component. Keeping them separate makes proposals and ROI easier to evaluate.
Should a clinic spend a fixed percentage of revenue on marketing?
A percentage can be a rough governance reference, but it should not replace service-level planning. Two clinics with the same revenue can have very different margins, capacity, competition and growth priorities.
Should I increase Google Ads spend if leads are cheap?
Not automatically. Check whether the leads are qualified, answered quickly, booked and attended. Cheap enquiry volume can be expensive if the clinic’s landing page, response process or targeting produces low-value demand.
What should a clinic marketing budget report include?
At minimum: spend by channel, qualified enquiries, response metrics, booked appointments, attendance or downstream outcomes where available, plus the measurement limitations. Review by service line when possible.
Source and claim policy
This guide intentionally avoids invented market-wide budget benchmarks. Actual spend and acquisition economics vary by specialty, city, treatment value, competition, capacity, pricing, patient eligibility, media conditions and conversion performance. Use verified clinic data wherever possible.
Related MDS guides
Medical Marketing Agency Cost in Egypt
Separate agency pricing from the clinic’s total growth budget.
Google Ads for Doctors in Egypt
Build the paid-search layer around high-intent treatment demand.
Healthcare Website Conversion
Improve the pages and enquiry journey before scaling media.
Why Clinics Lose Leads After the Inquiry
Find response and follow-up leakage that can waste budget.
Do not scale spend faster than the clinic can absorb demand
MDS can map your service priorities, capacity, current acquisition channels, website conversion, reception response and measurement stack before recommending where incremental budget should go.
 MDS TeamHealthcare marketing, search, patient-journey and conversion editorial team at MDS Healthcare. This page is educational and does not replace legal, regulatory, medical or privacy advice.